Anesthesia
Introduction
What are the indications for general anesthesia is pediatric patients?
General anesthesia is defined by the American Society of Anesthesiologists as a “drug induced loss of consciousness during which patients are not arousable, even by painful stimulation” [1]. The indications for general anesthesia are therefore any condition is which the physician needs to completely control a patient’s airway, breathing or circulation, to reduce recall and in order to allow the physician adequate time to finish the appropriate operation.
see also Sedation and Analgesia
Epidemiology
How many infants and children get anesthesia per year?
Approximately six million pediatric patients undergo general anesthesia annually. Twenty-five percent of these patients are infants [2].
General anesthesia has been safely given to children for many years. Improvements in inhalational and intravenous agents have increased the safety profile of general anesthesia and complication rates are low. General anesthesia has also allowed children to undergo painful or anxiety inducing procedures (e.g., dental procedures) in relative comfort.
Basic Science
What are commonly used inhalational agents?
Inhalational agents act by potentiating inhibitory GABA-A and glycine receptors while inhibiting excitatory channels, producing dose-dependent CNS, cardiovascular, and respiratory depression. Sevoflurane is the agent of choice for pediatric inhalational induction because of its low blood solubility and non-pungency, allowing for single breath or incremental mask induction [3][4]. With the single breath technique, the eyelash reflex is lost roughly 33% faster than with stepwise concentration increases, and it has a mild positive chronotropic effect that offers some protection against bradycardia. It is degraded by CO2 absorbents to compound A, but clinically significant nephrotoxicity has not been demonstrated in humans [5].
Nitrous oxide is a weak, highly insoluble adjuvant with anxiolytic properties that can speed sevoflurane induction via the second-gas effect. It is also frequently used to mask the odor of sevofluane at the start of an inhalation induction and to reduce the concentration of the primary agent required. However, it possibly could induce diffusion hypoxia at emergence (the Fink effect), postoperative nausea, and vomiting.
What are commonly used intravenous agents?
Propofol acts chiefly at GABA-A receptors, providing rapid loss of consciouslness, less post operative nausea and vomiting than volatiles, and precise control of anesthetic depth. Its disadvantages are pain on injection, and with prolonged high dose infusion, propofol infusion syndrome [6][7]. Notably, its pharmacokinetics are age- and size-dependent, so no single infusion model could fit all patients.
Remifentanil is an ultra-short-acting μ-opioid metabolized by nonspecific plasma/tissue esterases. Clearance of remifentanil is greater in infants than in older children, making it predictable and useful for procedures needing rapid recovery; though it can produce bradycardia, hypotension, and acute opioid tolerance. It is highly synergistic with propofol in total intravenous anesthesia.
Pathophysiology
What physiologic differences in infants and children should be considered with general anesthesia?
Ocular
Retinopathy of prematurity is typically found in infants exposed to supplemental oxygen and it is therefore important to limit the inspired oxygen concentration during anesthesia [8].
Respiratory
Oxygen consumption in neonates is more than 6 mL/kg, about twice that of adults, doubling the alveolar ventilation. In order to compensate for this, anesthesiologists need to increase the respiratory rate. Another factor to contend with during anesthesia can be severe tracheomalacia making mask ventilation difficult. After general anesthesia infants are more prone to apnea [9]. (see Complications)
Cardiovascular
Neonates convert from a fetal circulation (high pulmonary vascular resistance and low systemic vascular resistance) to adult circulation (pulmonary vascular resistance decreases while peripheral vascular resistance rises) in the first days to weeks of life. A state of transitional circulation exists in early infancy where factors such as hypoxia, hypercarbia, and changes in peripheral vascular tone can cause reversion to fetal circulation with an increase in pulmonary hypertension. This can cause very young children to have prolonged hypoxemic events when exposed to anesthesia.
Neonates also have a limited cardiac function secondary to reduced ventricular compliance and less ability to increase contractility [10] so they are dependent on their heart rate to increase cardiac output. Bradycardia is therefore poorly tolerated due to a lack of ability to increase cardiac output. The most common cause of bradycardia is hypoxemia [10].
In preterm and term infants, the parasympathetic system is predominant and stimulation of the vagus nerve by direct laryngoscopy or hypoxia can cause bradycardia.
Distribution of body water
During first year of life, total body water (TBW) constitutes 80% body weight and decreases to 60% by the first year. TBW and extracellular fluid (ECF) are increased proportionately in neonates with ECF about twice that of adults. ECF becomes similar to that of adults at 18 to 24 months. Infants have an increased metabolic rate and accelerated turnover of ECF which has implications for intraoperative fluid replacement. This increased total body water and larger volume of distribution contributes to a longer drug elimination half life.
Renal
Neonates have immature renal function that does not reach adult levels until approximately two years of age. Infants are obligate sodium losers and cannot concentrate urine which has implications for electrolyte balance during the perioperative period. They are also slower to excrete and are sensitive to volume overload. Clearance of renally excreted agents is delayed compared to older children and adults.
Thermoregulation
Infants are vulnerable to hypothermia due to a large ratio of body surface area to weight and limited ability to cope with cold stress. Brown fat metabolism is highly utilized for thermoregulation in infancy; this may be limited in premature or sick infants. Furthermore, anesthetic agents can interfere with brown fat metabolism. Exogenous sources of heat are needed to help maintain thermoregulation as hypothermia is associated with slower emergence and hypoxemia.
It is also important to not overheat infants as this can worsen cerebral damage secondary to other events such as hypoxemia and hypotension.
Liver
The hepatic system is not fully mature in infancy. Lower enzyme activity and lower albumin and binding protein levels create greater free drug levels in very young children.
What physiologic differences in infants and children should be considered with regional anesthesia?
The cardiovascular effects of regional anesthesia are minimal making it an ideal modality for certain procedures. Children require decreased minimum anesthetic concentration to block impulse conduction. This is due to thinner myelin sheaths, smaller fiber diameter, and shorter internodal distance. Accordingly, smaller doses of local anesthesia should be given. There is an increased risk of toxicity with local anesthetics - particularly in very young children.
What are the physiological changes brought on by general anesthesia?
The most consistently characterized physiological event brought on by anesthesia is impairment of thermoregulation. Volatile agents, intravenous agents, nitrous oxide, and opioids all substantially inhibit central thermoregulatory control. These agents each do so centrally, as each greatly and synchronously lowers the vasoconstriction and shivering thresholds while sparing the sweating threshold [11]. This central inhibition of tonic vasoconstriction produces anesthetic induced vasodilation, and in the first hour of anesthesia, core temperature drops from the redistribution of heat from the warm central components of the body to the periphery [12]. Infants, in particular, are are susceptible to these temperature changes, due to their body surface to volume ratio, being physically uncovered for the first 30-60 minutes following induction of anesthesia, and the cold environments of the operating rooms [12]. This mild hypothermia prolongs drug effects, can impair coagulation, increase the risk of wound infections, and raises plasma catecholamine levels [13]. Beyond thermoregulation, general anesthesia and surgical stress trigger neuroendocrine stress responses with release of cortisol and vasopressin activating RAAS (renin-angiotensin-aldosterone system), inducing perioperative water retention.
Prevention
What adjuncts or special methods can decrease the use of general anesthesia?
Regional and neuraxial anesthesia has been used in addition to or instead of general anesthesia. This is particularly helpful in premature infants undergoing inguinal hernia repair. Systematic review shows that spinal anesthesia in addition to sedation, instead of general anesthesia, reduces the risk of postoperative apnea by up to 47% in this patient group [9]. Spinal anesthesia can be used in conjunction with sedation for other lower abdominal, urological, and lower extremity procedures. Regional and neuraxial anesthesia can also be used in conjunction with general anesthesia to reduce the overall dose of general anesthetic agents required, improve postoperative pain control, and decrease postoperative nausea and vomiting.
Classification
What are the different types of anesthesia?
There are three main types of anesthesia - local, regional and general.
Local anesthesia is the use of medication to block sensation to a small area of the body. Medication can be applied (i.e., topical) or injected. Local anesthetics are depolarizing agents which block nerve conduction by altering the sodium and potassium cation exchange. Local anesthetics have less side effects and are generally safer than regional or general anesthesia.
Regional anesthesia is the utilization of medication to block sensation to a region of the body. Nerve blocks, spinal anesthesia, and epidural anesthesia are all considered regional anesthetics. Regional anesthesia is often used in conjunction with sedation to decrease anxiety and awareness.
Nerve blocks occur when local anesthesia is injected into a nerve bundle to block sensation to a body part. They are commonly used for procedures on single extremities. Nerve blocks provide adequate anesthesia without the broader hemodynamic complications from spinal, epidural, or general anesthesia.
For spinal anesthesia, medication is injected into the spinal fluid and produces numbness below the injection. Spinal anesthesia may last one to six hours depending in the medication injected. Epidural anesthesia is similar to spinal anesthesia except that a catheter is placed within the epidural space to allow for repeated dosing of medication. Epidural anesthesia is often used for postoperative pain relief after abdominal or thoracic procedures. Both spinal and epidural anesthesia may be associated with hypotension and urinary retention, and the dose of medication may need to be adjusted to treat these common side effects.
General anesthesia is a complete loss of consciousness with amnesia, analgesia and neuromuscular blockade. It can be divided into three phases: induction, maintenance and emergence. Induction usually occurs with inhalational anesthetic in children until intravenous access occurs. Propofol, etomidate and ketamine are often used for induction. Maintenance of anesthesia occurs with inhalational or intravenous medications. Common inhalational anesthetics include nitrous oxide, sevoflurane, or desflurane. Common intravenous medications used for maintenance are propofol and remifentanil. Emergence occurs as the body returns to consciousness and may result in a autonomic hyper-responsiveness which can be controlled with narcotics, beta blockers, and lidocaine.
Presentation
What preanesthetic evaluation do children need?
Evaluating a pediatric patient prior to the administration of anesthesia is an essential component of preoperative care in order to determine a child’s fitness to endure anesthesia. It is during this visit that one can identify something that may prohibit or delay proceeding with an operation. The preoperative evaluation includes a thorough history and physical exam.
A history of prematurity, sickle cell anemia, asthma, bronchopulmonary dysplasia, gastrointestinal motility disorders, recent upper respiratory infections, intraventricular hemorrhage, or cystic fibrosis should raise a red flag to the evaluator. Risk factors associated with an increased risk of a perioperative respiratory event should be determined including a history of recent respiratory symptoms, pre-existing pulmonary disorders, anemia, eczema, morbid obesity, a family history of asthma/eczema, or tobacco smoke exposure [14][15]. All pre-existing comorbidities should be optimized prior to going forward with an elective procedure.
The preoperative evaluation is also the time to address patient or family anxiety. Special programs (e.g., child life counselors) are available to assist with this aspect of preoperative care.
Preoperative laboratory studies are not necessary for elective procedures in otherwise healthy children but should be obtained in children with comorbidities or undergoing moderate to high risk procedures. A preoperative hemoglobin value may be helpful in children undergoing procedures with a possibility for large volume blood loss, patients with a history of anemia, prior premature infants, and patients younger than six months of age at least 3-4 weeks prior to surgery [16]. Routine preoperative chest radiographs are not needed.
How does the age of the patient effect the doses of anesthetic given?
Newborns are very sensitive to anesthetic agents and their drug metabolism is inefficient. Their response to agents is variable due to differences in the volume of distribution, sensitivity of the central nervous system and varying levels of protein. After the first month of life, drug metabolism increases so much that higher doses of anesthetics are needed compared to older children and adults. In fact, inhaled anesthetic dosage is nearly double to maintain general anesthesia.
How does the patient’s postconceptual age effect the scheduling of elective surgery and administration of anesthetic?
Postoperative apnea is well documented in premature infants and neonates and occurs in five to 49% of infants undergoing surgery [17][18][19]. The risk of apnea decreases with increasing postconceptional age (PCA) - decreasing to less than five percent after a PCA of 50 weeks in late preterm infants (35 to 37 weeks gestational age) and 52 weeks in early preterm infants (32 weeks gestational age). The optimal timing of elective surgery is unknown. The risks of apnea must be weighed against the benefit of the surgery itself and individual cases will vary.
A 2015 trial randomized patients less than 60 weeks PCA to regional versus general anesthesia for hernia repair. No difference in overall apnea was identified although patients undergoing general anesthesia were more likely to have early apnea (within 30 minutes). Prematurity was the strongest predictor of apnea and was found in 96% of patients with apnea [20]. Current recommendations are that premature infants undergoing general anesthesia at less than 60 weeks PCA should have postoperative cardiorespiratory monitoring for at least 12 hours, although institutional variations exist that may utilize a slightly lower PCA threshold [21][22].
A 2026 systematic review and meta-regression (Dalal, Coté, et al.) confirmed postmenstrual age is the strongest and most consistent predictor of postanesthesia apnea, with recommended monitoring durations ranging from 6 to 24 hours depending on PCA[23]A retrospective cohort of infants after inguinal hernia repair found respiratory complications in 35.5% of preterm infants <45 weeks PCA, but only 5.9% in those 45–60 weeks PCA — and within that 45–60 week group, complications clustered in infants with a respiratory history (e.g., bronchopulmonary dysplasia: 13.2% vs 0.7%), with lower gestational age predictive [24]. The data support using gestational age, anemia (hematocrit <30%), respiratory history, and documented recovery-room apnea — not PCA alone — to individualize admission.
Sevoflurane is commonly used in infants due to its low side effect profile. Neuromuscular blockade is avoided when possible. Propofol and drugs which are metabolized in the liver clear slower in premature infants. Therefore, drug dose should be slowly titrated up to the desired effect.
Assessment
How are anesthetic risk factors classified?
The risk factors for anesthetic mortality include neonates, age less than one year, American Society of Anesthesiologists (ASA) III and IV classification, children undergoing emergency surgery, general anesthesia, and cardiac surgery [25][26]. Airway management problems and cardiopulmonary events account for the majority of the cases of anesthesia-related mortality in children with comorbidities[26]. Though there can be inter-rater variability between these scores, they have been shown to correlate with perioperative complications and mortality [27].
| ASA classification | patient status |
| 1 | normal healthy patient |
| 2 | patient with mild systemic disease |
| 3 | patient with severe systemic disease |
| 4 | patient with severe systemic disease that is a constant threat to life |
| 5 | moribund patient who is not expected to survive without an operation |
| 6 | declared brain dead patient whose organs are being removed for donor purposes |
| E | emergency modifier for any ASA classification when failure to immediately correct a medical condition poses risk to life or organ viability |
Anatomy
Which pediatric patients are at risk of having a difficult airway?
The pediatric airway differs from the adult airway and it is imperative to anticipate the differences when caring for children. The pediatric tongue is larger and the mandible is smaller than in adults increasing the risk of obstruction. An oral airway can allow for ventilation. The larynx is more cephalad (C2 to C4), decreasing the distance from the oropharynx to the larynx, which may lead to obstruction or dislodgement of the endotracheal tube (ETT). The epiglottis is floppy and may obstruct the view of the vocal cords during intubation. The pediatric airway is also more anterior making it more difficult to see with laryngoscopy. The cricoid cartilage is the most narrow point of the pediatric airway and can cause difficulty in passing the ETT after traversing the vocal cords. Also, the anterior vocal cords are attached more caudally, making the cords slanted and more likely to limit ETT passage. (see also Respiratory Care Anatomy)
Many congenital anomalies may be associated with a difficult airway and these can be divided into upper airway obstructions, craniofacial anomalies, and difficult airways associated with syndromes.
The causes of upper airway obstruction include tonsillar hypertrophy, choanoal atresia or stenosis, laryngomalacia and vascular or cystic lesions.
Craniofacial anomalies include cleft lip and palate, mandibular hypoplasia, the enlarged tongue seen with Beckwith-Wiedemann syndrome, and many others. It is important to anticipate difficulty in mask ventilation as well as endotracheal intubation. Other patients may have conditions which limit extension of the neck, such as patients with trisomy 21 or spinal anomalies.
There are a few notable syndromes with difficult airways which should be discussed and coordinated with anesthesia prior to scheduling a surgical procedure. Pierre-Robin is mandibular hypoplasia which can cause airway obstruction and sometimes occurs with a cleft palate as well. These patients’ airways may improve with age and symptoms of airway obstruction should be elicited from parents prior to anesthesia. Treacher-Collins is a mandibulofacial dysostosis which causes mandibular, maxillary and zygomatic hypoplasia. These patients may also have ear and eye defects as well as cardiovascular and renal anomalies. Craniofacial dysostosis occurs with Aperts syndrome. These patients may present with craniosynostosis, maxillary hypoplasia, tracheal, and vertebral anomalies.
It is imperative to have the plan, premedication, equipment, and personnel available when addressing a difficult airway. Multiple different sized endotracheal tubes should be available as well as bronchoscopes and laryngeal mask airways. The amount of time to secure an airway is limited in children with a decrease in oxygen saturation below 90% in four minutes for infants weighing 10 kg versus 10 minutes in a 70 kg adult. Fiberoptic bronchoscopy is the optimal tool for the difficult airway but it may not be available in the unanticipated difficult airway. Alternative techniques include blind nasotracheal intubation and tactile oral or nasal intubation.
Prenatal Concerns
Prenatal Care
What agents are typically used for anesthesia in fetal surgery?
Fetal surgery can be divided into minimally invasive procedures, open midgestational procedures, and ex utero intrapartum therapy (EXIT) [29]. Anesthesia ranges from local to regional to general anesthesia. Minimally invasive techniques such as those for twin to twin transfusion syndrome can be done with intravenous tocolysis, preoperative indomethacin, and light sedation. More advanced minimally invasive procedures such as balloon dilations may require general anesthesia for the mother and intramuscular fentanyl, vecuronium, and atropine for the fetus.
Open midgestational procedures require complete uterine relaxation with high dose volatile anesthetics such as desflurane or remifentanil in conjunction with propofol. Once the fetus is exposed, intramuscular injections of fentanyl, vecuronium, and atropine should be given. The fetal oxygen saturation ranges from 40 to 70% and cardiac monitoring may be necessary. Fetal bradycardia, maternal or fetal bleeding, and maternal blood pressure changes must be closely monitored.
EXIT procedures utilize similar anesthesia techniques initially but do not need postoperative tocolytics and fluid administration can be generous since the baby will be delivered. Two anesthesia circuits are necessary and separate operating rooms may be needed. After securing the fetal airway and clamping the umbilical cord, the uterine relaxation must be reversed to allow the uterus to clamp down and control bleeding.
Medical Treatment
What are the typical anesthetic agents given to children?
Inhalational agents
Inhalational agents are often used for both the induction and maintenance of anesthesia. Hemodynamic changes are often seen when inhalational agents are used and therefore these agents are avoided in patients with cardiovascular compromise. When no comorbidity exists, the use of inhalational agents is quite safe.
Nitrous oxide is often used in conjunction with other inhalational agents and can augment the uptake of these agents during the induction of anesthesia. It is less potent than the others and its concurrent use allows for decreased dosage of other agents, thereby minimizing their hemodynamic effects. It has a quick onset and recovery. Nitrous oxide has been shown to distend gas containing spaces and therefore is not recommended to be used in patients where this would be perilous; including pneumocephalus, intestinal obstructions, and pneumothoraces.
Halothane is an effective inhalational agent that is infrequently used today as it has significant cardiovascular effects including bradycardia, hypotension and ventricular ectopy. It also causes bronchodilation. It has an effect on epinephrine such that it sensitizes the heart to the epinephrine-induced arrhythmias.
Isoflurane is an agent not frequently used as it can cause significant airway irritability. It has a low solubility coefficient so induction can be performed quickly. It also has effects of hypotension and bradycardia but is better tolerated than halothane.
Desflurane is a potent agent but has substantial deleterious effects on the airway with subsequent risks of laryngospasm, cough, and oxygen desaturation in the pediatric population.
Sevoflurane is currently the most commonly used inhalational agent in infants and children. It is an effective agent that has a low solubility coefficient and a rapid emergence time. It is well tolerated, in that it is associated with less hemodynamic alterations, and is a bronchodilating agent. Sevoflurane is metabolized by the cytochrome system within the liver and may cause renal diabetes insipidus.
Neuromuscular blocking agents
Muscle relaxants block the nicotinic acetylcholine receptor site at the neuromuscular junction. They are used for both induction and maintenance. Their use can decrease the amount of inhalational or intravenous sedation needed. Succinylcholine is a fast acting depolarizing agent, while rocuronium, vecuronium, ciasatracurium, pancuronium, and mivacurium are nondepolarizing agents.
Succinylcholine has several untoward effects that limit its use in the pediatric population. It can initiate malignant hyperthermia, severe hyperkalemia, myoglobinemia, and increased intraocular pressure. Rarely, a child may have a pseudocholinesterase deficiency which can lead to sustained paralysis for up to eight hours. Its use should be limited to emergency procedures and excluded in patients with muscular dystrophy, polytrauma, burns, spinal cord injury or a personal or familial predisposition to malignant hyperthermia.
The nondepolarizing agents are better tolerated and require reversal at the end of the procedure. Each of the nondepolarizing medications has a different metabolic, excretory, and side effect profile that should be considered for an individual patient.
Intravenous agents
Propofol is a sedative and hypnotic medication commonly used for both induction and maintenance. It has a rapid rate of onset and clearance and is thereby well tolerated. It can cause dose-dependent hypotension that typically resolves after discontinuation. Continuous propofol injection can seldom lead to a phenomenon termed propofol infusion syndrome which can include metabolic acidosis, rhabdomyolysis, hyperkalemia and rarely mortality. Long term utilization of the medication is prohibited in children. Historically, an infusion of more than 4 mg/kg/h (about 67 mcg/kg/min) for more than 48 hours was an upper limit for the drug in order to avoid the syndrome. This comes from the early pediatric ICU case series (1998 analysis) of children sedated with propofol [30]. Most reported cases fall in that range: prolonged high-dose sedation in critically ill children. However, the threshold is not a safe line. Cases have been reported at lower doses and after shorter infusions, including a handful after a few hours of intraoperative use[31]. The risk reflects the dose and duration together with the clinical context.
Ketamine is a N-methyl-D-aspartate receptor antagonist that is frequently used for bedside procedures as an analgesic and amnestic. The intravenous dose typically lasts approximately five to eight minutes. It causes a dissociation that can lead to hallucinations and can cause an increase in cardiac index, hypertension, tachycardia and intraocular and intracranial pressure.
Etomidate can also be used intravenously and is well tolerated as it has negligible cardiovascular or respiratory effects. Its effect on adrenal insufficiency is controversial and the clinical significance of this has been shown to be trivial in the pediatric population [32][33].
What is the role of local anesthesia?
Topical anesthesia is a form of local anesthesia and can be used for simple superficial procedures. Sedation is not needed for its administration. The most common is a eutectic mixture of local anesthetics (EMLA), and is made up 2.5% lidocaine and 2.5% prilocaine. It is optimally applied with an occlusive dressing, at least 60 minutes prior to a minor procedure, such as incision and drainage of an abscess.
Infiltration anesthesia can be administered by the surgeon or anesthesiologist prior to the start of a procedure. This can be used without any sedation in a cooperative child or after sedation for a more invasive procedure. Infiltration can be given to the general field of a procedure (e.g., wound infiltration) and has been shown to have good analgesic effects for minor procedures. Side effects are avoided when dosage guidelines are followed.
The three most commonly used kinds of local anesthetic utilized are lidocaine, bupivacaine, and ropivacaine. Bupivacaine is commonly used in the pediatric population as it has a longer duration of action than lidocaine and offers more sensory than motor block. Overdose leads to both cardiotoxicity in the form of arrhythmias and neurotoxicity typically in the form of seizure or coma. Ropivacaine is similar to bupivacaine in that it is a more selective sensory rather than motor block and is better tolerated in terms of cardiac side effects; however, it has increased cost.
Local anesthetic dosages are based on weight, age and the duration of the procedure.
| agent | maximum dose (mg/kg) |
| lidocaine | 4.5 |
| bupivacaine | 2.5 |
| ropivacaine | 3.0 |
Adjuncts administered with these agents (e.g., clonidine, epinephrine and dexmedetomidine) are used to prolong the duration of the analgesia given a constant dose. Local anesthetic toxicity syndrome occurs with overdosage or intravascular injection. Due to the reduced level of serum binding proteins, infants less than six months of age will have higher levels of free drug. Symptoms of toxicity are neurologic and cardiac in nature and can include tremors, tinnitus, seizures, and arrhythmias. This can be treated by a bolus (1.5 mL/kg) and continuous infusion (0.25 mL/kg/min) of 20% intralipid emulsion.
What is the role of regional anesthesia?
Local anesthetic can also be infiltrated around a specific peripheral nerve, plexus, or neuraxial region (i.e., caudal, spinal, and epidural block) – this is known as regional anesthesia.
Regional anesthesia in children has been shown to be safe and the risk of complication is approximately 1:100, overall [34]. Most complications have little or no long term sequelae. The use of ultrasonography guidance for regional anesthesia has escalated and its use provides visualization of anatomic structures, leading to more effective analgesia. A recent Cochrane review reported ultrasound guidance increases the success rate and block duration with a greater benefit seen in younger children [35].
Regional anesthesia can be used alone (e.g., premature infants undergoing inguinal hernia repair) or in conjunction with general anesthesia. The use of regional anesthesia along with general anesthesia reduces the amount of general anesthetic required and allows for less respiratory, cardiovascular and neurologic depression as well as a smoother emergence and faster wake up times [36]. This is particularly helpful in high risk populations such as children with neuromuscular, cardiac, or chronic lung disease. Regional anesthesia is associated with good hemodynamic stability intraoperatively and reduces the need for postoperative ventilator support. It may also reduce the stress response to pain, intraoperative blood loss, and the duration of postoperative bowel dysfunction [34].
Postoperative regional anesthesia can provide excellent short- or long-term pain control and can reduce postoperative opiate use. This is turn reduces the risk of opiate related respiratory depression and apnea.
Contraindications for neuraxial and regional blocks include coagulopathy, local (at the site of injection) or systemic infection, increased intracranial pressure, or coexisting congenital anomaly of the spine or meninges.
Caudal block
Caudal blocks are the most commonly performed neuraxial block in children weighing less than 30 kg. This block is a type of epidural blockade and is performed by accessing the epidural space through the sacral hiatus between the sacrum and coccyx. It is utilized to administer anesthesia and/or analgesia below the umbilical region (i.e., T10 dermatome). Its use in older children is limited, as calcifications form within the sacrococcygeal ligament, making access to this space more challenging. Caudal blocks are typically used as a single injection of local anesthetic prior to the start of the procedure although a catheter can be placed for continuous infusion as well. Continuous caudal infusion used as the only anesthetic agent has been reported to be both safe and effective in elective procedures such as inguinal hernia repair [37]. The complications of a caudal block include injection of anesthetic into the intravascular or intraosseous space, unintended spinal block, and pelvic hematoma.
The anatomic landmark for the caudal epidural block is the sacral canal, formed by the sacrococcygeal membrane and sacral cornua, typically easy to palpate in neonates and infants [38]. With the pediatric patient in the lateral decubitus position and hips flexed, the needle is advanced through the sacrococcygeal membrane, then flattened and advanced minimally into the caudal canal. This is followed by aspiration to exclude blood or CSF before injection of anesthesia [39].
Spinal anesthesia
Spinal anesthesia involves injection of anesthetic directly into the cerebrospinal fluid of the spinal subarachnoid space. It can be used as surgical anesthesia to replace general anesthesia for procedures below the T10 dermatome that last less than 60 to 90 minutes. Relatively low dosages are needed to get an adequate anesthetic effect, there is a rapid rate of onset and it can be used with the addition of an opiate for postoperative pain control. The downside of the spinal anesthetic is the risk of performing a "high spinal" in which the cardiopulmonary system is affected. Additionally, it is a one time administration and a catheter for longer term infusion cannot be used. Postdural puncture headaches have been described. Its most common use is for preterm infants less than 60 weeks postconceptual age or full term infants less than 44 weeks postconceptual age to reduce postoperative apnea. A 2015 Cochrane review reported spinal anesthesia reduces the risk of postoperative apnea in preterm infants undergoing inguinal hernia repair in early infancy by up to 47% when compared to general anesthesia [9].
Epidural catheters
Epidural analgesia can be administered via a caudal, lumbar, or thoracic route. It is used as a supplement for general anesthesia as well as for postoperative pain control. Indications for continuous epidural analgesia include open thoracic surgery, major intra-abdominal surgery with visceral dissection, spinal surgery, and long term pain management [40]. These indications are currently being scrutinized as the use of peripheral regional anesthesia is increasing.
Repair of pectus excavatum via the Nuss or Ravitch procedures are effective but associated with significant postoperative pain. Epidural analgesia has been used to minimize this pain, but there is clear evidence that intercostal nerve cryoablation combined with local nerve block is a superior analgesic method, with significantly reduced LOS, opioid use, and pain scores [41] [42] [43] [44].
(see also Pectus Excavatum Postoperative Care)
Peripheral nerve blocks
Peripheral nerve blocks are gaining acceptance and are replacing neuraxial blocks in various procedures. Trunk blocks can be for both thoracic and abdominal procedures. These include paravertebral, serratus, transversus abdominis plane (TAP), rectus sheath, and ilioinguinal/iliohypogastric nerve blocks.
The paravertebral block allows for blockade of multiple spinal intercostal nerves. It is used for postoperative pain control following chest wall and breast procedures as well as rib fractures.
The ilioinguinal-iliohypogastric block anesthetizes these two named nerves and is mainly used for genitourinary procedures and inguinal hernia repairs. It can be achieved blindly or though an ultrasound-guided technique, and covers the cutaneous regions of the ipsilateral groin.
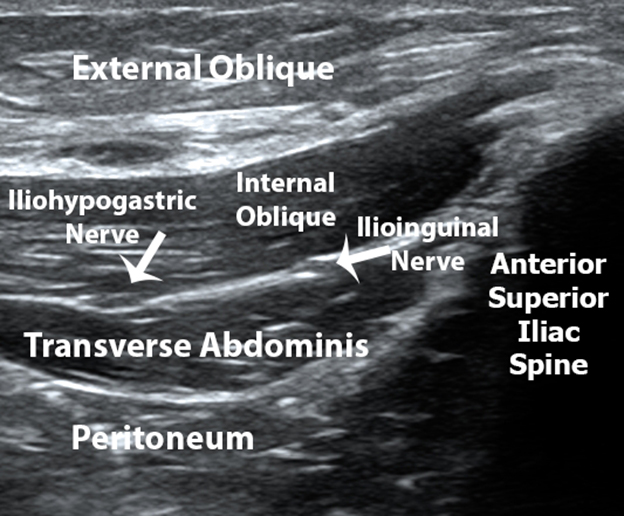
The TAP block is used to block the terminal intercostal portions of T8 through L1 somatic afferent nerves between the internal oblique and transverse abdominis muscles. It provides analgesia to the abdominal wall skin, muscle, fascia, and parietal peritoneum and can be used for the majority of abdominal procedures.
The rectus sheath block (RSB) anesthesizes the anterior rami of T7 through T12 or the somatic nerves of the umbilical region. Its application is therefore mainly for umbilical procedures such as umbilical hernia repair or laparoscopic procedures with umbilical port sites. A recent report from a single institution showed pre-incision RSB for single incision laparoscopic appendectomies decreased opioid consumption and minimized pain scores when compared to local anesthetic infiltration. The block added approximately six minutes to the procedure [45].
A recent meta-analysis of ten randomized trials utilizing the TAP block and RSB demonstrated that the use of these blocks reduces pain and opiate use in the pediatric population [46].
Specific extremity blocks for both the upper and lower extremities can be utilized including interscalene, supraclavicular, infraclavicular, axillary, lumbar, iliac fascia, and selective nerves such as the ulnar, median, radial, sciatic, and femoral.
A penile block is mainly used for circumcision and other procedures of the distal penis such as simple hypospadias repair. Vasoconstrictors (e.g., epinephrine) should not be used as an additive in this location. A single injection to the dorsal nerve or a ring block at the base of the penis superficial to the Buck fascia is used.

Medical Decision Making
What are some of the advantages of the most common anesthetic agents?
Inhalational agents
Pediatric patients have more rapid uptake and elimination of inhaled anesthetics than adults due to their increased respiratory rate and cardiac index. Sevoflurane has a low blood solubility which causes a rapid uptake and elimination with fast induction and recovery. It is equal to other inhaled agents in terms of risk of laryngospasm and causes less cardiac depression than halothane. Sevoflurane can also increase intracranial pressure, making it less ideal in neurosurgical cases or in children with head trauma.
Isoflurane causes less myocardial depression than other agents with a preservation of heart rate. It causes a greater reduction in the cerebral metabolic requirement for oxygen and peripheral vascular resistance. Isoflurane causes more laryngospasm than other less pungent agents.
Desflurane has very low solubility, which leads to faster emergence.
Intravenous agents
Propofol causes a decrease in arterial blood pressure due to arterial vasodilation and reduced sympathetic tone. It may also effect myocardial contractility. The effects of propofol on the central nervous system include cerebral vasoconstriction in proportion to the dose. This reduces cerebral blood flow and the metabolic demand for oxygen. Propofol also causes a dose-dependent respiratory depression.
Surgical Decision Making
What is the best anesthetic managment of a patient with an anterior mediastinal mass?
The most commonly encountered anterior mediastinal masses include non Hodgkin and Hodgkin lymphoma; however, thymic tumors, germ cells tumors, neurogenic tumors, and vascular malformations can be encountered. A tissue diagnosis is often needed in order to correctly guide therapy. Unfortunately, the induction of general anesthesia in patients with a mediastinal mass can have fatal consequences due to cardiopulmonary collapse from compression of the airway and obstruction of venous return / cardiac output. A multidisciplinary team should manage these patients which includes pediatric surgeons, oncologists, anesthesiologists, intensivists and radiation oncologists. A preoperative computerized tomography (CT) scan of the chest is essential in understanding risk. Pulmonary function tests may be helpful.
Predicting which patients will suffer complications from general anesthesia is challenging. Tracheal cross sectional area less than 50% of predicted on CT scan and peak expiratory flow rates of 50% predicted or less have been shown to preclude safe induction of general anesthesia [47]. The presence of symptoms, including preoperative stridor, and imaging findings of tracheal cross sectional area less than 30% of normal or less than 70% associated with bronchial compression have been reported as risk factors [48]. Additional reports deem tracheal compression, three or more respiratory signs or symptoms, vascular compression and concurrent infection to be risk factors for general anesthesia administration with tracheal compression being the strongest factor [49]. One such categorization [50][51][52]
- Low risk — asymptomatic, no radiographic airway or cardiovascular compression (general anesthesia safe)
- Intermediate risk — mild-to-moderate dyspnea/orthopnea, tracheal compression <70%, no bronchial compression (multidisciplinary evaluation)
- High risk — orthopnea, stridor or cyanosis, tracheal compression >70% (or tracheal CSA ≤30% of normal with bronchial compression), great-vessel compression, or tamponade physiology (multidisciplinary evaluation, avoid GA if at all possible)
Algorithms have been put forth to deal with these challenging situations. The general guideline is to start with the safest site that gives a diagnosis: thoracentesis/pleural fluid flow cytometry when effusion is present, peripheral blood or bone marrow, or sampling of an accessible peripheral lymph node under local anesthesia.
If a patient demonstrates airway or cardiovascular obstruction at presentation, recommendations include biopsy under local anesthesia with cardiovascular bypass available. If possible, obtaining tissue from sites other than the anterior mediastinal mass should be considered, such as extrathoracic lymph node biopsy or percutaneous needle aspiration of pericardial or pleural fluid. Procedures such as these have been reported to minimize anesthetic risks and complications [53]. If this method for biopsy is not feasible and symptoms exist, the use of preoperative empiric therapy such as radiation can be used to decrease the size of the mass and risk of cardiopulmonary collapse. However, empiric therapy can alter histopathology and lead to inappropriate diagnosis or staging. If a patient does not have symptoms, biopsy using a local anesthetic would be the first recommendation; however, if this cannot be done, general anesthesia with bypass on standby may be necessary. Emergent use of salvage sternal elevation has been reported in cases of unanticipated intraoperative cardiorespiratory collapse [50] .
What are the physiologic effects of pneumoperitoneum?
Laparoscopy has become the mainstay of many pediatric surgical procedures. Studies have been done dedicated to infants and their response to laparoscopy. Laparoscopy involves insufflation of CO2 to achieve pneumoperitoneum which increases intra-abdominal pressure and can impact diaphragmatic mobility, decreases functional residual capacity and pulmonary compliance, increases airway resistance, and decreases tidal volume and minute ventilation. Additionally, CO2 is absorbed systemically leading to an increase in pCO2 and a decrease in pH. These effects require desufflation or an increase in ventilation [54]. Additionally, age varies inversely with the absorption of CO2 during laparoscopic procedures [55].
The respiratory effects of CO2 insufflation are directly proportional to the increase in insufflation pressure. Ventilatory changes are frequently necessary with rising airway pressures required to restore a baseline tidal volume and pCO2. This can occur with no long term sequelae. It can be concluded that laparoscopy can be performed safely in infants with minimal long term clinical consequences, as long as any cardiorespiratory changes are tended to appropriately by the anesthesiologist throughout the procedure [56].
What are the effects of single lung ventilation during thoracoscopy?
Video assisted thoracoscopic surgery has gained acceptance over the past decade for procedures such as lobectomy, tracheoesophageal repair, and congenital diaphragmatic hernia repair. Single lung ventilation is a technique utilized to improve the exposure and working conditions during technically complex procedures in children. Multiple techniques exist to perform single lung ventilation, including bronchial main stem intubation, double lumen endotracehal tubes, and bronchial blockers. The decision of which technique to use is based on patient age and size. If single lung ventilation cannot be obtained (e.g., small infants), CO2 insufflation alone may be sufficient.
Single lung ventilation has been shown to be safe and effective in the pediatric population [57]. These authors also investigated the hemodynamic and respiratory effects in piglets receiving single lung ventilation with CO2 hemipneumothorax. They report stable mean arterial pressures and no critical incidents. Despite a decrease in cardiac index, preload, and intrathoracic blood volume, single lung ventilation with CO2 insufflation was clinically well tolerated.[58]
A recent report investigated patients undergoing thoracoscopic lobectomy and compared patients undergoing single versus double lung ventilation. Patients with a lesion in the lower lobe and those undergoing atypical resections preferably had double lung ventilation. Single lung ventilation was performed in patients greater than 2200 g, those with an infection or tumor, without any major cardiopulmonary comorbidities, and a lesion located in the upper, middle, or all lobes. There was no difference in conversion to thoracotomy, prompt extubation, or postoperative atelectasis. There was no mortality or major cardiopulmonary events in either group. The authors conclude that either single or double lumen ventilation can be performed with a comparable safety profile [59].
What are the special considerations in emergent pediatric anesthesia?
Emergency surgery in the pediatric population requires an astute and experienced anesthesiologist to assure safe and effective anesthesia. Basic principles to protect and establish a stable airway and administering medications for anesthesia while caring for and not contributing to any hemodynamic instability. Fluid and blood products are often administered preoperatively and throughout the procedure. The supplemental use of vasopressors is frequently required to control low blood pressure. Vascular access is warranted in the form of large bore peripheral or central venous lines. Obtaining access can be difficult in an under resuscitated, dehydrated child and advanced skills may be needed, such as a cutdown or an intraosseous line.
Airway management during a pediatric emergency requires a rapid sequence intubation (RSI). If the airway is a component of the emergent nature of the procedure, advanced airway techniques such as awake intubation, nasal intubation, or cricothyroidotomy may be needed. Patients are treated as though they have a full stomach and the rapid sequence of preoxygenation, cricoid pressure, intravenous induction agents with paralysis and endotracheal intubation is essential. The risks of RSI include inability to intubate, cardiovascular effects of medications, and rapid desaturations in neonates and infants [60][61].
Preoperative Preparation
Which children need a preoperative anesthesia consult?
A preoperative evaluation by an anesthesiologist should be considered for each patient undergoing anesthesia. Patients with comorbidities that may affect the administration of anesthetic agents should be evaluated by an anesthesiologist. Examples of this are patients undergoing complex cardiothoracic surgeries. Patients with a personal history or family history of anesthetic-related complications, significant metabolic, endocrine, or hematologic abnormalities, or those with a proclivity to develop an anesthetic complication such as muscular dystrophy or metabolic disorder should be seen as well. Additionally, those with an anatomic anomaly that may affect the establishment of a safe airway should be seen (e.g., facial or maxillary abnormalities, intraoral pathology, reduced neck mobility). Any patient with an ASA status greater than III would benefit from an anesthesia consultation.
How long do pediatric patients need to remain NPO prior to general anesthesia?
The ASA "2-4-6-8" rule remains the current US standard for healthy children undergoing elective procedures: 2 hours for clear liquids, 4 hours for breast milk, 6 hours for infant formula/nonhuman milk/a light meal, and 8 or more hours for fried/fatty foods or meat. These minimum fasting intervals apply across all ages in healthy (ASA I--II) patients and were carried forward in the 2023 update [62]. In the 2023 update, the ASA explicitly considered reducing the pediatric clear-liquid fast from 2 h to 1 h but concluded that, due to low-quality evidence, it could not formally recommend the shorter interval. European (ESPA/ESAIC), Canadian (CAS), Australian/New Zealand (ANZCA), and UK (APA) societies have moved to a 1-hour clear-liquid fast in children [63] [64].
How do recent upper respiratory tract infections impact the safety of general anesthesia?
Respiratory events are a leading cause of perioperative morbidity and mortality in the pediatric population [65]. Children receiving general anesthesia with a current or recent upper respiratory tract infection (URI) are more likely to experience a perioperative respiratory adverse event. This is thought ot be secondary to an increase in airway hyperreactivity. The presence of an upper respiratory infection has been shown to increase postoperative hypoxemic events [66][67]. Additionally, laryngospasm, bronchospasm, atelectasis, coughing, airway obstruction, stridor and breath holding have a higher incidence. These effects have been shown to increase costs and length of stay [68][69]. Infants with respiratory syncitial virus infections appear to be at specially high risk [70] The long term sequelae from these events are unclear.
How long should one wait after a viral upper respiratory tract infections before having anesthesia?
There is no standardized guideline dictating an appropriate interval to wait after a viral URI. Various factors are relevant and must be included in the decision including the urgency of the procedure and certain institutional and patient factors.
Perioperative respiratory adverse event (PRAE) risk is highest during the first 2 weeks after a URTI. The landmark von Ungern-Sternberg cohort [15] found children with current symptoms or symptoms within 2 weeks had a relative risk of ~2.0-2.3, and concluded rescheduling 2-3 weeks after a URTI is a safe approach [71].
Rather than fixed waiting times, current practice increasingly uses validated scoring. The COLDS score (Current symptoms, Onset of symptoms, Lung disease, airway Device, Surgery) integrates these domains; a score ≥16 has the strongest association with PRAEs, though each institution is advised to set its own rescheduling cutoff. This tool was highlighted in 2026 pediatric anesthesia guidance on adenotonsillectomy error traps [72][73].
A retrospective study found a symptom-free period of at least 1-2 weeks reduced PRAEs, and that abnormal preoperative chest imaging was a strong independent predictor [73]
Lower respiratory tract infection warrants a longer delay - generally 4 weeks or until symptoms resolve - and certain infections (e.g., pertussis, M. pneumoniae) may justify postponing up to 3 months because of prolonged airway hyperreactivity and cough [74].
Steps of the Procedure
| Block | Target/Landmarks | Ultrasound Approach | References |
| Paravertebral block | Wedge-shaped paravertebral space lateral to the vertebral body/transverse process | Probe identifies transverse process, pleura, and costovertebral ligament; in-plane needle inserts local anesthesia with pleural depression | |
| Ilioinguinal-iliohypogastric block | Superior and medial to ASIS; nerves between internal oblique m. and transverse abdominis m. | Linear probe over anterior abdominal wall, needle advances into the interfascial plane around both nerves using in-plane or out-of-plane technique | |
| TAP block | Neurovascular plane between internal oblique and transverse abdominis (T10-L1) | Linear probe between costal margin and iliac crest; in-plane needle hydrodissection of the TAP plane | |
| Rectus sheath block | Between rectus abdominis and the posterior rectus sheath (T9-T11) | Lienar probe lateral to umbilicus; in-plane needle introduced into the long axis parallel to the probe. Slowly advance until the lateral border of the rectus is reached, until the tip of the needle is seen between the posterior aspect of rectus abdominis and its sheath | |
| Extremity blocks (axillary/infraclavicular, femoral, sciatic, median) | Perineural deposition around the nerve’s standard landmarks | Linear or hockey-stick probe, real-time visualization via in-plane or out-of-plane approach to acheive circumfrential perineural spead | |
| Penile block | Dorsal nerves of the penis in the subpubic space to Scarpa’s fascia at the base | Hockey-stick probe placed transversely, needle advanced using an in-plane approach from the lateral aspect into the subpubic space bilaterally |
Intraoperative Decision Making
What is laryngospasm?
Laryngospasm occurs when the intrinsic laryngeal muscles undergo reflex constriction, which triggers glottic closure. It can occur at induction of anesthesia, during endotracheal intubation, and at extubation. This can lead to an inability to adequately ventilate, resulting in hypercarbia, hypoxia, pulmonary edema and eventual cardiac collapse which can be fatal. It is a frequently encountered complication of inhalational anesthesia in the pediatric population. The incidence of laryngospasm varies inversely with age; with children more likely to undergo laryngospasm than adults, and infants suffering this complication more frequently than older children. Those with comorbidities such as asthma or an upper respiratory infection, or those with passive smoke exposure tend to have higher rates as well.
Certain techniques of the anesthesiologist can aid in minimizing the risk of laryngospasm. Awareness of the aforementioned risk factors can assure a sufficient depth of anesthesia prior to any potential trigger such as intubation. Extubation should be performed either when the patient is still deep or fully awake. Extubation between these two phases can lead to laryngospasm. Lidocaine can prevent laryngospasm and both the intravenous and topical forms are beneficial [86]. Atropine and magnesium have been described as preventative agents but further studies are needed [87][88].
Timely diagnosis of laryngospasm is critical. Treating laryngospasm initially involves conservative measures such as stopping any ongoing surgical procedure or trigger, suctioning the larynx of any debris, and deepening anesthesia. Continuous positive airway pressure at 1.0 FiO2 is administered via face mask. If this does not improve the laryngospasm, a muscle relaxant is necessary. This is typically in the form of intramuscular or intravenous succinylcholine. This leads to relaxation of the vocal cords and proper ventilation.
How should intraoperative fluid, electrolytes and glucose be managed in the pediatric patient?
The goals of fluid and electrolyte management in the perioperative child are to provide maintenance fluids and replace pre- and intra-operative fluid loss.
In 1957, Holliday and Segar proposed, based on caloric needs, daily replacement fluids for children between zero to 10 kg of 100 mL/kg, for patients weighing 11 to 20 kg, 1000mL plus 50 mL/kg for each kg between 11 and 20 kg, and for children greater than 20 kg, 1500 ml plus 20 mL/kg for each kg greater than 20 kg. This has become the basis for what is now known as the “4-2-1 rule” of fluid therapy and continues to be used for maintenance fluid therapy in the perioperative period [89].
Estimating preoperative fluid deficit due to NPO status and the replacement of that fluid has been somewhat controversial. With current recommendations limiting preoperative fasting to as short as possible, evidence suggests that children should be able to maintain normal intravascular volume [90][91].
Traditionally, the choice of intravenous fluids has been hypotonic solution with 5% glucose added. Recent studies, however, reveal that this may lead to significant hyponatremia and hyperglycemia [90][92]. Therefore, current recommendations are for use of an isotonic solution with one to 2.5% dextrose, which has been shown to avoid acid base imbalance, hyponatremia, and hyperglycemia in infants and toddlers. This isotonic, low glucose recommendation has been advocated in guidelines published by the Association of the Scientific Medical Societies of Germany [91]. In patients at higher risk for hypoglycemia (i.e., neonates, children on hyperalimentation, or those with endocrine pathologies) frequent monitoring of blood glucose levels is recommended with adjustment of the rates of infusion [90][91].
There is limited data for the use of colloids in children. German guidelines recommend the use of colloid when crystalloid alone is insufficient to maintain normovolemia when blood products are not indicated. They do note, however, that the use of colloids are associated with more adverse drug reactions when compared to crystalloid solutions [91].
(see also Fluid and Electrolytes)
How should blood products be utilized intraoperatively in the pediatric patient?
Blood product transfusion is associated with the risk of viral infection although these risks have decreased over the past several decades. Noninfectious risks include transfusion related acute lung injury, immunosuppression and, in cases of massive transfusions, metabolic derangements including hyperkalemia, metabolic alkalosis, hypocalcemia, and hypochloremia [93][94]. These noninfectious risks account for 87% to 100% of fatal transfusions [93].
When comparing indications for transfusion in children based on hemoglobin levels, various studies have shown that a restrictive transfusion policy (i.e., transfusion for hemoglobin less than 7 g/dL) fare no worse and potentially do better than those children transfused at a higher hemoglobin levels [95][96][97]. Patients in a restrictive transfusion group suffered fewer transfusion events and donor exposures [95].
(see also Transfusion and Coagulation Therapy)
How should pediatric patients be monitored?
For simple procedures, pulse oximetry, capnography, blood pressure, electrocardiogram, and body temperature are sufficient. For more complex operations, serial blood gas analyses will assist in determining acid base status, and glucose levels and central venous catheters can be used to determine intravascular volume [91]. These guidelines have been endorsed by the American Society of Anesthesiologists [98].
Postoperative Care
What are the indications for admission after general anesthesia?
The risk of postoperative apnea is highest in premature infants undergoing elective operations with gestational and postconceptual age found to be inversely related to apnea risk (discussed at length above) [99]. The age at which elective general surgical procedures can be performed as an outpatient varies between 44 to 60 weeks postconceptual age depending on the study. Factors such as a history of bronchopulmonary dysplasia and preoperative anemia increased the risk of postoperative apnea and for these infants and postoperative monitoring overnight is recommended even in older infants [99][100].
Postoperative monitoring should include continuous pulse oximetry and heart rate monitoring.
Complications
What are the complications associated with general anesthesia?
Assessment of anesthetic risk in children has been estimated by the American Society of Anesthesia risk assessment score [28]. The ASA can help identify patients preoperatively that may be at higher risk for anesthetic complications and allow adjustment to the anesthetic plan for these higher risk children.
Pulmonary aspiration can be a devastating event although studies have shown that the incidence of aspiration in children is relatively low - two per 10,000 cases in elective procedures and 2.2 per 10,000 in emergency operations [101]. Laryngospasm is common in pediatric surgical patients, with twice the incidence compared to adults. Studies have found that in children from birth to nine years of age, the incidence is 17 in 1000 cases. In children with obstructive lung disease or upper respiratory infections, the risk can be up to 64 to 96 per 1000 cases [102]. There is evidence to suggest that the use of supraglottic airway devices can decrease the incidence of laryngospasm [103].
Postoperative apnea is more commonly seen in former preterm infants.
The current consensus is that a single, brief general anesthetic in infancy does not cause measurable cognitive impairment, but repeated or prolonged exposure before age 3 is associated with a small increased risk of specific deficits - most consistently ADHD, behavioral, and motor problems.
Anesthesia in infants and neurodevelopmental risks
The most recent synthesis, an October 2026 narrative review in Lancet Child & Adolescent Health covering 2019-2025 evidence, concludes that randomized trials show no measurable harm from a single short exposure, while observational studies report mixed findings and population-based studies consistently identify a small increased ADHD risk after early exposure [104]. Importantly, interpretation is confounded by the underlying surgical indication and comorbidities, and the review emphasizes that necessary procedures should not be delayed because of theoretical neurodevelopmental risk [104] .
What have RCTs shown about the neurodevelopmental risk of anesthesia in infancy?
GAS trial: Infants ≤60 weeks PCA randomized to awake-regional vs. sevoflurane general anesthesia (median duration 54 min) for hernia repair showed equivalent full-scale IQ at 5 years and equivalent Bayley cognitive scores at 2 years. This was felt to be strong evidence of equivalence [105] .
PANDA study: Sibling-matched cohort with a single anesthetic exposure before 36 months showed no significant differences in IQ or in memory, motor/processing speed, attention, executive function, language, or behavior at ages 8 to 15 [106].
MASK study: Examining multiple exposures, it found no difference in the primary outcome of general intelligence. For secondary outcomes, processing speed and fine motor abilities were decreased in multiply but not singly exposed children; other domains did not differ. The parents of multiply exposed children reported increased problems related to executive function, behavior, and reading [107] .
However, a 2022 JAMA Network Open systematic review/meta-analysis found that exposure was preferentially associated with certain subdomains rather than global impairment. Behavioral problems showed the largest effect, with significant deficits in fine and gross motor function and an increased hazard of ADHD diagnosis [108].
Repeated exposure carries higher risk: learning disability risk was ~35% with repeated anesthesia vs. ~20% with a single exposure before age 4; a single exposure resembled anesthesia-naive outcomes. Duration of a single anesthetic (even >181 min) did not independently affect outcomes in one analysis, whereas multiple independent exposures did [109].
The FDA December 2016 Drug Safety Communication (labeling change for 11 GABA/NMDA-active agents including sevofurane, propofol, ketamine, benzodiazepines, and barbiturates) warned that repeated or lengthy (>3 hours) use in children under 3 or in the third trimester may affect brain development, driven largely by animal neuroapoptosis data; the FDA stated short, single exposures are unlikely to cause harm [110][111].
The 2026 AAP guidance on the pediatrician’s role reaffirms that available evidence suggests a single, short anesthetic in a child under 3 does not cause significant neurodevelopmental deficits, while acknowledging the behavioral/ADHD/motor signals seen with repeated exposure remain confounded by comorbidity [112].
A clear and consistent message is: "Do not delay medically necessary procedures over theoretical risk." It is reasonable to consider deferring truly elective procedures until the child is older when feasible.
Systematic review of infant anesthesia risks video from the 2019 APSA annual meeting
What are the complications associated with regional anesthesia?
Multi-institutional database reviews in the United States, France and the United Kingdom have established a very low rate of complication for regional anesthesia [113][114][115].
In the Pediatric Regional Anesthetic Network, risks and complications were divided into single injection regional blocks and catheter associated blocks. The PRAM study reviewed 14,917 regional blocks in 13,725 patients. In patients receiving single injection blocks, the most common complication noted in this group (overall incidence of three percent, accounting for 57% of adverse events) was the inability to place the block or failure of the block to work. Other complications included two blocks lasting greater than 12 hours, one episode of a positive test dose and another block with positive blood aspiration. Acute complications were more frequent in the catheter group, though the most common complications were catheter related (dislodgement or kinking) accounting for 26% of adverse events, for an overall incidence of two percent of the total group. Other catheter associated risks included local inflammation or infection (11%), positive test doses or vascular puncture (2%), accidental dural puncture (0.9%), Horner syndrome in patients receiving thoracic catheters (0.6%) and paresthesia (0.1%) [113].
These studies note that there were no identified long term risks of regional blocks. Of the complications noted, the majority resolved within the hospital stay and no sequelae lasted greater than three months. This evidence supports that regional anesthetic use in children is very safe with low risks without long term effects.
Both caudal and epidural blocks can cause urinary retention and lower extremity weakness.
What is malignant hyperthermia?
Malignant hyperthermia (MH) is a rare inherited metabolic disorder triggered by inhalation agents and/or succinylcholine. These triggers cause an unregulated release of calcium from skeletal muscle cells resulting in acidosis, hyperthermia, hypermetabolism, and rhabdomyolysis. The incidence is 1 in 3,000 to 15,000 children. The mortality rate for untreated MH is 80%. Treated, MH has a mortality rate of approximately three percent in children. Risk factors for MH include a positive family history, Duchenne muscular dystrophy, and mitochondrial disorders [116].
The treatment of MH relies on early diagnosis to prevent worsening symptoms. Classic signs include tachycardia, ventricular dysarrhythmia, tachypnea, rigidity and elevated temperature. Laboratory values will show hyperkalemia, hypercarbia, increased lactate and myoglobinuria. Patients undergoing general anesthesia with early signs (e.g., tachypnea, tachycardia, increased end tidal carbon dioxide) should be treated aggressively. Management includes stopping inhalation agents, hyperventilation with 100% oxygen, cooling, and intravenous dantrolene (2.5 mg/kg, repeated as needed). In addition, treatment should be initiated for correction of hyperkalemia, ventricular arrhythmia, and metabolic acidosis.
Outcomes
How safe is general anesthesia?
The use of general anesthesia in pediatric patients has a complication rate ranging from 0.01 to 3.5% [117]. The rate of complications are highest in preterm infants [118][119]. The most common complications are respiratory and include airway obstruction, laryngospasm, or bronchospasm, desaturation and apnea. Cardiovascular complications are rare in healthy children and include arrhythmias and hypotension. Longer procedures and higher anesthetic dose increase the risk of complications [117].
The mortality attributable to general anesthesia in children ranges from 0.1 to 1.4 per 10,000 [120]. The Japanese Society of Anesthesiologists Committee on Operating Room Safety has reported data over the last two decades and published a rate of perioperative death associated to anesthetic management of 0.1/10,000 for otherwise healthy children undergoing elective surgery [121]. The Mayo Clinic looked at 92,881 children undergoing anesthesia and the overall cardiac arrest rate attributed to anesthetic management was 0.65/10,000 [122]. The highest risk for cardiac arrest were neonates and patients undergoing cardiac procedures. The increased mortality is attributed to a more complex patient group.
Perspectives and Commentary
To submit comments about this topic please contact the editors at think@apsapedsurg.org.
Glossary
Eyelash reflex - It signals unconsciousness, not adequate depth. Losing the reflex puts the child in stage II anesthesia, where airway reflexes are hyperactive. The corneal reflex, by comparison, is lost at a deeper plane (stage III).
Compound A - Compound A is fluoromethyl-2,2-difluoro-1-(trifluoromethyl)vinyl ether, sometimes abbreviated PIFE. It is a haloalkene that forms when the strong bases in CO₂ absorbents, particularly NaOH and KOH, strip hydrogen fluoride from sevoflurane. In rats, it is nephrotoxic. There is very low risk of this in children due to high fresh gas flows, short operations, and most institutions use absorbents that don’t contain strong bases.
Second gas effect - This is the faster rise in the alveolar concentration of one anesthetic gas when it is given together with a high concentration of a rapidly absorbed gas, which in practice is nitrous oxide. The classic example is 60 to 70 percent N₂O combined with sevoflurane for inhalational induction. It works through the concentration effect of the first gas. Nitrous oxide is given at such a high concentration, and is taken up so quickly, that a large volume of gas leaves the alveoli for the blood in the first minutes. Two things then occur -> 1) alveolar volume shrinks, so the gases left behind (sevoflurane and oxygen) are concentrated into a smaller volume and their partial pressures rise, and 2) the lost volume is replaced by fresh gas brings in more of the second agent.
Discussion Questions and Cases
To submit interesting cases which display thoughtful patient management please contact the editors at think@apsapedsurg.org.
The following questions were created with the aid of AI:
Question 1
A 6-year-old boy with no significant medical history undergoes general anesthesia with sevoflurane and a single dose of succinylcholine for a laceration repair. Approximately 25 minutes into the case, the anesthesiologist notes a rising end-tidal CO₂ that does not abate with increased minute ventilation, sinus tachycardia, generalized muscle rigidity, and masseter spasm. Core temperature has risen from 36.8°C to 39.1°C over 10 minutes.
What is the most appropriate immediate management?
A. Continue the volatile anesthetic, deepen sedation, and apply surface cooling
B. Discontinue triggering agents, hyperventilate with 100% O2, and administer IV dantrolene 1 mg/kg (repeat until signs resolve, up to 10 mg/kg)
C. Administer IV dantrolene 2.5 mg/kg once and continue the sevoflurane at a reduced concentration
D. Administer antipyretics and a non-depolarizing neuromuscular blocker to relieve rigidity
E. Switch from sevoflurane to desflurane and give a fluid bolus
Correct answer: B
Discussion
The earliest and most reliable sign of acute malignant hyperthermia (MH) is an unexplained rise in end-tidal CO₂ refractory to increased ventilation, accompanied by tachycardia, muscle/masseter rigidity, and a later rapid temperature rise [123]. The immediate steps are: (1) discontinue all triggering agents (volatile anesthetics and succinylcholine), (2) deliver 100% oxygen at high flow and hyperventilate, and (3) give dantrolene by rapid IV push at a minimum of 1 mg/kg, repeating until the hypermetabolic signs subside or a cumulative maximum of 10 mg/kg is reached. The pediatric dose is the same as the adult dose. Supportive measures include active cooling, treating hyperkalemia and dysrhythmias, managing metabolic acidosis, and promoting diuresis to protect against myoglobinuric kidney injury.
Post-crisis: Oral or IV dantrolene 4-8 mg/kg/day in divided doses for 1-3 days is recommended to prevent recrudescence, which occurs in roughly 14-20% of cases [124] . All suspected events should be referred to a specialized MH center for muscle contracture and/or genetic testing of the patient and family.
Question 2
A 4-year-old girl is scheduled for an elective inguinal hernia repair. During the preoperative visit, the mother reports that the child’s maternal uncle "nearly died from a high fever during surgery". The child has never had anesthesia and appears healthy.
What is the most appropriate approach?
A. Proceed with a standard sevoflurane inhalational induction, since the child herself has never reacted
B. Cancel surgery permanently until genetic testing excludes an RYR1 variant
C. Treat the child as MH-susceptible: obtain IV access, provide a non-triggering (trigger-free) anesthetic, prepare a clean/flushed anesthesia machine, monitor core temperature, and have dantrolene immediately available
D. Give prophylactic dantrolene 10 mg/kg and then proceed with a standard volatile-based anesthetic
E. Require a muscle contracture (IVCT) biopsy on the 4-year-old before any anesthetic can be given
Correct answer: C
Discussion
MH is inherited (most commonly autosomal-dominant RYR1-related), so a first- or second-degree relative with a credible MH history makes this child MH-susceptible until proven otherwise, and she should be managed as if she has MH regardless of testing status [125]. Because inhalational/mask induction with volatile agents is contraindicated, the child requires preoperative IV access so a trigger-free IV induction and maintenance can be used, avoiding all potent volatile agents and succinylcholine [112][125]. Preparation includes a dedicated non-triggering anesthetic plan (regional techniques are safe), flushing/preparing the anesthesia machine per manufacturer guidance or using activated-charcoal filters, continuous electronic core temperature monitoring for any general anesthetic exceeding ~30 minutes, and ensuring an adequate dantrolene supply and MH cart are immediately available. Routine prophylactic dantrolene is no longer recommended when a non-triggering technique is used (option D). Surgery need not be cancelled or deferred pending biopsy - the child can undergo a safe non-triggering anesthetic now - so options B and E are incorrect. The family should also be counseled, given MedicAlert identification, and referred to an MH center for evaluation [126].
Key steps when a positive (family) history is identified:
1. Elicit a detailed personal and family anesthetic history; treat suspected susceptibility as confirmed.
2. Flag inhalational/mask induction as contraindicated and plan for preoperative IV access.
3. Avoid all triggers: potent volatile agents (halothane, sevoflurane, desflurane, isoflurane, enflurane) and succinylcholine.
4. Prepare the anesthesia machine (flush/charcoal filters) or use a dedicated clean machine; consider scheduling as the first case.
5. Monitor core temperature; have dantrolene and a stocked MH cart immediately available.
6. Provide MedicAlert identification and refer the patient/family to a specialized MH center for genetic ± contracture testing.
References
- Continuum of Depth of Sedation:Definition of General Anesthesia and Levels of sedation/Analgesia. October 15, 2014. Retreived on December 20, 2016. http://www.asahq.org/~/media/sites/asahq/files/public/resources/standards-guidelines/continuum-of-depth-of-sedation-definition-of-general-anesthesia-and-levels-of-sedation-analgesia.pdf.
- Sun LS, Li G, DiMaggio CJ, et al. Feasibility and pilot study of the Pediatric Anesthesia NeuroDevelopment Assessment (PANDA) project. J Neurosurg Anesthesiol. 2012;24(4):382-8. [PMID:23076226]
- Edgington TL, Muco E, Maani CV. Sevoflurane. StatPearls. StatPearls Publishing; 2022. [PMID:30521202]
- Lerman J. Induction of anesthesia with sevoflurane in children: Curiosities and controversies. Paediatr Anaesth. 2022;32(10):1100-1103. [PMID:35899582]
- Patel SS, Goa KL. Sevoflurane. A review of its pharmacodynamic and pharmacokinetic properties and its clinical use in general anaesthesia. Drugs. 1996;51(4):658-700. [PMID:8706599]
- Singh A, Anjankar AP. Propofol-Related Infusion Syndrome: A Clinical Review. Cureus. 2022;14(10):e30383. [PMID:36407194]
- Guo J, Jin X, Wang H, Yu J, Zhou X, Cheng Y, Tao Q, Liu L, Zhang J. Emergence and Recovery Characteristics of Five Common Anesthetics in Pediatric Anesthesia: a Network Meta-analysis. Mol Neurobiol. 2017 Aug;54(6):4353-4364.
- McGregor ML, Bremer DL, Cole C, et al. Retinopathy of prematurity outcome in infants with prethreshold retinopathy of prematurity and oxygen saturation >94% in room air: the high oxygen percentage in retinopathy of prematurity study. Pediatrics. 2002;110(3):540-4. [PMID:12205257]
- Jones LJ, Craven PD, Lakkundi A, et al. Regional (spinal, epidural, caudal) versus general anaesthesia in preterm infants undergoing inguinal herniorrhaphy in early infancy. Cochrane Database Syst Rev. 2015;6:CD003669. [PMID:26058963]
- Barash PG, Cullen BF, and Stoelting RK. Clinical Anesthesia. Philadelphia: Lippincott Williams & Wilkins, 2006. Print
- Sessler DI. Perioperative thermoregulation and heat balance. Lancet. 2016;387(10038):2655-2664. [PMID:26775126]
- Amy E. Vinson, Walid Alrayashi, Constance S. Houck; Educational Perspectives: Anesthesia 101: What the Neonatologist Needs to Know About Anesthesiology. Neoreviews January 2020; 21 (1): e1–e13. https://doi.org/10.1542/neo.21-1-e1
- Mekonnen MT, Mustofa SY, Berhe YW, et al. Intraoperative pediatrics hypothermia and its factors during general anesthesia at comprehensive specialized hospitals, Northwest Ethiopia: Multicenter follow up study. PLoS One. 2025;20(5):e0320950. [PMID:40327603]
- Subramanyam R, Yeramaneni S, Hossain MM, et al. Perioperative Respiratory Adverse Events in Pediatric Ambulatory Anesthesia: Development and Validation of a Risk Prediction Tool. Anesth Analg. 2016;122(5):1578-85. [PMID:27101501]
- von Ungern-Sternberg BS, Boda K, Chambers NA, et al. Risk assessment for respiratory complications in paediatric anaesthesia: a prospective cohort study. Lancet. 2010;376(9743):773-83. [PMID:20816545]
- Goobie SM, Gallagher T, Gross I, Shander A. Society for the advancement of blood management administrative and clinical standards for patient blood management programs. 4th edition (pediatric version). Pediatr Anesth. 2019; 29: 231–236. https://doi.org/10.1111/pan.13574
- Liu LM, Coté CJ, Goudsouzian NG, et al. Life-threatening apnea in infants recovering from anesthesia. Anesthesiology. 1983;59(6):506-10. [PMID:6650906]
- Malviya S, Swartz J, Lerman J. Are all preterm infants younger than 60 weeks postconceptual age at risk for postanesthetic apnea? Anesthesiology. 1993;78(6):1076-81. [PMID:8512100]
- Davidson AJ, Disma N, de Graaff JC, et al. Neurodevelopmental outcome at 2 years of age after general anaesthesia and awake-regional anaesthesia in infancy (GAS): an international multicentre, randomised controlled trial. Lancet. 2016;387(10015):239-50. [PMID:26507180]
- Davidson AJ, Morton NS, Arnup SJ, et al. Apnea after Awake Regional and General Anesthesia in Infants: The General Anesthesia Compared to Spinal Anesthesia Study--Comparing Apnea and Neurodevelopmental Outcomes, a Randomized Controlled Trial. Anesthesiology. 2015;123(1):38-54. [PMID:26001033]
- Faraz A. Khan, Tim Jancelewicz, Kathleen Kieran, Saleem Islam, COMMITTEE ON FETUS AND NEWBORN, SECTION ON SURGERY, SECTION ON UROLOGY; Assessment and Management of Inguinal Hernias in Children. Pediatrics July 2023; 152 (1): e2023062510. 10.1542/peds.2023-062510
- Templeton TW, Sommerfield D, Hii J, Sommerfield A, Matava CT, von Ungern-Sternberg BS. Risk assessment and optimization strategies to reduce perioperative respiratory adverse events in Pediatric Anesthesia—Part 2: Anesthesia-related risk and treatment options. Pediatr Anesth. 2022; 32: 217–227.
- Dalal PG, Malviya S, Coté CJ, et al. Postanesthesia Apnea in Former Preterm and Term Infants: A Qualitative Systematic Review and Meta-analysis. Anesthesiology. 2026;144(6):1454-1469. [PMID:42117733]
- Massoud M, Kühlmann AYR, van Dijk M, et al. Does the Incidence of Postoperative Complications After Inguinal Hernia Repair Justify Hospital Admission in Prematurely and Term Born Infants? Anesth Analg. 2019;128(3):525-532. [PMID:29649028]
- Cronje L: A review of paediatric anaesthetic-related mortality, serious adverse events and critical incidents. Southern African Journal of Anaesthesia and Analgesia 21:6, 147-153 2015. DOI: 10.1080/22201181.2015.1119503
- Gonzalez LP, Pignaton W, Kusano PS, et al. Anesthesia-related mortality in pediatric patients: a systematic review. Clinics (Sao Paulo). 2012;67(4):381-7. [PMID:22522764]
- Sankar A, Johnson SR, Beattie WS, et al. Reliability of the American Society of Anesthesiologists physical status scale in clinical practice. Br J Anaesth. 2014. [PMID:24727705]
- American Society of Anesthesiologists. (2014, October). Retrieved December 17, 2016, from http://www.asahq.org
- Lin EE, Tran KM. Anesthesia for fetal surgery. Semin Pediatr Surg. 2013;22(1):50-5. [PMID:23395146]
- Bray RJ. Propofol infusion syndrome in children. Paediatr Anaesth. 1998;8(6):491-9. [PMID:9836214]
- Kill C, Leonhardt A, Wulf H. Lacticacidosis after short-term infusion of propofol for anaesthesia in a child with osteogenesis imperfecta. Paediatr Anaesth. 2003;13(9):823-6. [PMID:14617125]
- Sokolove PE, Price DD, Okada P. The safety of etomidate for emergency rapid sequence intubation of pediatric patients. Pediatr Emerg Care. 2000;16(1):18-21. [PMID:10698137]
- Du Y, Chen YJ, He B, et al. The Effects of Single-Dose Etomidate Versus Propofol on Cortisol Levels in Pediatric Patients Undergoing Urologic Surgery: A Randomized Controlled Trial. Anesth Analg. 2015;121(6):1580-5. [PMID:26496368]
- Bosenberg A. Benefits of regional anesthesia in children. Paediatr Anaesth. 2012;22(1):10-8. [PMID:21895855]
- Guay J, Suresh S, Kopp S. The Use of Ultrasound Guidance for Perioperative Neuraxial and Peripheral Nerve Blocks in Children: A Cochrane Review. Anesth Analg. 2016. [PMID:27308952]
- Anand KJ, Ward-Platt MP. Neonatal and pediatric stress responses to anesthesia and operation. Int Anesthesiol Clin. 1988;26(3):218-25. [PMID:3049395]
- Mueller CM, Sinclair TJ, Stevens M, et al. Regional block via continuous caudal infusion as sole anesthetic for inguinal hernia repair in conscious neonates. Pediatr Surg Int. 2016. [PMID:27873010]
- Marhofer P, Keplinger M, Klug W, et al. Awake caudals and epidurals should be used more frequently in neonates and infants. Paediatr Anaesth. 2015;25(1):93-9. [PMID:25265914]
- Wiegele M, Marhofer P, Lönnqvist PA. Caudal epidural blocks in paediatric patients: a review and practical considerations. Br J Anaesth. 2019;122(4):509-517. [PMID:30857607]
- Moriarty A. Pediatric epidural analgesia (PEA). Paediatr Anaesth. 2012;22(1):51-5. [PMID:22128779]
- Santos K, Aoke K, Shelar V, et al. Cryoanalgesia Plus Nerve Block Strategies versus Cryoanalgesia Alone in Patients with Pectus Excavatum Undergoing the Nuss Procedure: A Systematic Review and Meta-Analysis. Eur J Pediatr Surg. 2025;35(6):460-469. [PMID:40300759]
- Loftus PD, Elder CT, Russell KW, et al. Paravertebral regional blocks decrease length of stay following surgery for pectus excavatum in children. J Pediatr Surg. 2016;51(1):149-53. [PMID:26577910]
- Zobel MJ, Ewbank C, Mora R, et al. The incidence of neuropathic pain after intercostal cryoablation during the Nuss procedure. Pediatr Surg Int. 2020;36(3):317-324. [PMID:31760443]
- van Braak H, de Beer SA, de Jong JR, et al. Intercostal Nerve Cryoablation or Epidural Analgesia for Multimodal Pain Management after the Nuss Procedure: A Cohort Study. Eur J Pediatr Surg. 2024;34(6):488-492. [PMID:38242172]
- Maloney, C, Abd El-Shafy, I, Kallis, M, Lipskar, AM, Kars, M, Hagen, J. "Ultrasound-guided bilateral rectus sheath block vs. conventional local analgesia in single port laparoscopic appendectomy for children with non-perforated appendicitis." Moderated poster presentation at the Society for Pediatric Anesthesia, Colorado Springs, CO. April 2, 2016.
- Hamill JK, Rahiri JL, Liley A, et al. Rectus sheath and transversus abdominis plane blocks in children: a systematic review and meta-analysis of randomized trials. Paediatr Anaesth. 2016;26(4):363-71. [PMID:26846889]
- Shamberger RC. Preanesthetic evaluation of children with anterior mediastinal masses. Semin Pediatr Surg. 1999;8(2):61-8. [PMID:10344302]
- Hack HA, Wright NB, Wynn RF. The anaesthetic management of children with anterior mediastinal masses. Anaesthesia. 2008;63(8):837-46. [PMID:18547295]
- Ng A, Bennett J, Bromley P, et al. Anaesthetic outcome and predictive risk factors in children with mediastinal tumours. Pediatr Blood Cancer. 2007;48(2):160-4. [PMID:16317755]
- Jöhr M, Hölzle M, Malär AU. Anesthesia for children with anterior mediastinal masses-sternal elevation as rescue method. Paediatr Anaesth. 2022;32(4):580. [PMID:35150171]
- Honda M, Yuki A, Takahiro H, et al. Predictive risk score of respiratory complications in children with mediastinal tumors: A case-control study. Cancer Med. 2023;12(2):1167-1176. [PMID:35748036]
- Tan A, Nolan JA. Anesthesia for children with anterior mediastinal masses. Paediatr Anaesth. 2022;32(1):4-9. [PMID:34714957]
- Acker SN, Linton J, Tan GM, et al. A multidisciplinary approach to the management of anterior mediastinal masses in children. J Pediatr Surg. 2015;50(5):875-8. [PMID:25783332]
- Bozkurt P, Kaya G, Yeker Y, et al. The cardiorespiratory effects of laparoscopic procedures in infants. Anaesthesia. 1999;54(9):831-4. [PMID:10460552]
- McHoney M, Corizia L, Eaton S, et al. Carbon dioxide elimination during laparoscopy in children is age dependent. J Pediatr Surg. 2003;38(1):105-10; discussion 105-10. [PMID:12592630]
- Bannister CF, Brosius KK, Wulkan M. The effect of insufflation pressure on pulmonary mechanics in infants during laparoscopic surgical procedures. Paediatr Anaesth. 2003;13(9):785-9. [PMID:14617119]
- Bataineh ZA, Zoeller C, Dingemann C, et al. Our experience with single lung ventilation in thoracoscopic paediatric surgery. Eur J Pediatr Surg. 2012;22(1):17-20. [PMID:21960427]
- Witt L, Osthaus WA, Schröder T, et al. Single-lung ventilation with carbon dioxide hemipneumothorax: hemodynamic and respiratory effects in piglets. Paediatr Anaesth. 2012;22(8):793-8. [PMID:22171739]
- Dingemann C, Zoeller C, Bataineh Z, et al. Single- and double-lung ventilation in infants and children undergoing thoracoscopic lung resection. Eur J Pediatr Surg. 2013;23(1):48-52. [PMID:23093436]
- Sorbello M, Paternò DS, Zdravkovic I, et al. Pharmacological approach to rapid sequence induction/intubation: a contemporary perspective. Curr Opin Anaesthesiol. 2025;38(4):369-374. [PMID:40493782]
- Stein ML, Park RS, Kovatsis PG. Emerging trends, techniques, and equipment for airway management in pediatric patients. Paediatr Anaesth. 2020;30(3):269-279. [PMID:32022437]
- Joshi GP, Abdelmalak BB, Weigel WA, et al. 2023 American Society of Anesthesiologists Practice Guidelines for Preoperative Fasting: Carbohydrate-containing Clear Liquids with or without Protein, Chewing Gum, and Pediatric Fasting Duration-A Modular Update of the 2017 American Society of Anesthesiologists Practice Guidelines for Preoperative Fasting. Anesthesiology. 2023;138(2):132-151. [PMID:36629465]
- https://www.cochranelibrary.com/cdsr/doi/10.1002/14651858.CD013809.pub2/full
- Dalal PG, Malviya S, Cravero J, et al. Reviewing "Nil Per Os" Guidance for Clear Fluids in Children Before Anesthesia: Survey of the Pediatric Anesthesia Leadership Council. Anesth Analg. 2025;140(3):507-514. [PMID:39773771]
- Stepanovic B, Regli A, Becke-Jakob K, et al. Preoperative preparation of children with upper respiratory tract infection: a focussed narrative review. Br J Anaesth. 2024;133(6):1212-1221. [PMID:39358184]
- Levy L, Pandit UA, Randel GI, et al. Upper respiratory tract infections and general anaesthesia in children. Peri-operative complications and oxygen saturation. Anaesthesia. 1992;47(8):678-82. [PMID:1519717]
- Rolf N, Coté CJ. Frequency and severity of desaturation events during general anesthesia in children with and without upper respiratory infections. J Clin Anesth. 1992;4(3):200-3. [PMID:1610574]
- Tait AR, Malviya S, Voepel-Lewis T, et al. Risk factors for perioperative adverse respiratory events in children with upper respiratory tract infections. Anesthesiology. 2001;95(2):299-306. [PMID:11506098]
- Oofuvong M, Geater AF, Chongsuvivatwong V, et al. Excess costs and length of hospital stay attributable to perioperative respiratory events in children. Anesth Analg. 2015;120(2):411-9. [PMID:25517194]
- Wörner J, Jöhr M, Berger TM, et al. [Infections with respiratory syncytial virus. Underestimated risk during anaesthesia in infants]. Anaesthesist. 2009;58(10):1041-4. [PMID:19672564]
- Hii J, Templeton TW, Sommerfield D, et al. Risk assessment and optimization strategies to reduce perioperative respiratory adverse events in pediatric anesthesia-Part 1 patient and surgical factors. Paediatr Anaesth. 2022;32(2):209-216. [PMID:34897906]
- Percy S, Quinlan CA, Murto K, et al. Error Traps in Pediatric Adenotonsillectomy: Clinical Patterns, Cognitive Pitfalls, and Evidence-Informed Mitigation Strategies. Paediatr Anaesth. 2026;36(6):592-606. [PMID:41925058]
- Lee HJ, Woo JH, Cho S, et al. Risk Factors for Perioperative Respiratory Adverse Events in Children with Recent Upper Respiratory Tract Infection: A Single-Center-Based Retrospective Study. Ther Clin Risk Manag. 2020;16:1227-1234. [PMID:33363377]
- Rai E, Alaraimi R, Al Aamri I. Pediatric lower respiratory tract infection: Considerations for the anesthesiologist. Paediatr Anaesth. 2022;32(2):181-190. [PMID:34927318]
- Ortiz J, Wofford L. Analgesic Benefits of Ultrasound-Guided Thoraco-Abdominal Wall Peripheral Nerve Blocks . Open Anesthesiol J, 2016;
- Kumar R, Mohammed S, Paliwal B, et al. The midpoint transverse process to pleura (MTP) block for postoperative analgesia in patients undergoing modified radical mastectomy: A case series. J Anaesthesiol Clin Pharmacol. 2023;39(4):648-650. [PMID:38269175]
- Abdellatif AA. Ultrasound-guided ilioinguinal/iliohypogastric nerve blocks versus caudal block for postoperative analgesia in children undergoing unilateral groin surgery. Saudi J Anaesth. 2012;6(4):367-72. [PMID:23493806]
- Aksu C, Yörükoğlu HU, Cesur S, et al. Pediatric fascial plane blocks: an educational review with technique, tips & tricks. BMC Anesthesiol. 2025;25(1):320. [PMID:40596847]
- The POCUS Atlas. (n.d.). Transversus Abdominis Plane (TAP) Block. Retrieved September 9, 2026, from https://www.thepocusatlas.com/tap.
- Chen L, Liu S, Cao Y, et al. Rectus sheath block versus local anesthetic infiltration in pediatric laparoscopic inguinal hernia repair: a randomized controlled trial. Int J Surg. 2023;109(4):716-722. [PMID:36974687]
- Alsaeed AH, Thallaj A, Khalil N, et al. Ultrasound-guided rectus sheath block in children with umbilical hernia: Case series. Saudi J Anaesth. 2013;7(4):432-5. [PMID:24348296]
- Delvi MB. Ultrasound-guided peripheral and truncal blocks in pediatric patients. Saudi J Anaesth. 2011;5(2):208-16. [PMID:21804805]
- C. Dadure, X. Capdevila, Continuous peripheral nerve blocks in children, Best Practice & Research Clinical Anaesthesiology, Volume 19, Issue 2, 2005, Pages 309-321, ISSN 1753-3740, https://doi.org/10.1016/j.bpa.2004.11.001.
- Jun Takeshita, Atsuto Saeki, Hirofumi Hamaba, Kazuya Tachibana. Dorsal penile nerve block via injection into the subpubic space using a short-axis in-plane approach: A technical description,
JCA Advances, Volume 3, Issue 2, 2026, 100209, ISSN 2950-5534. https://doi.org/10.1016/j.jcadva.2026.100209.
(https://www.sciencedirect.com/science/article/pii/S2950553426000122) - McPhee AS, McKay AC. Dorsal Penile Nerve Block. [Updated 2023 Feb 18]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2026 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK535389/
- Mihara T, Uchimoto K, Morita S, et al. The efficacy of lidocaine to prevent laryngospasm in children: a systematic review and meta-analysis. Anaesthesia. 2014;69(12):1388-96. [PMID:24992191]
- Gulhas N, Durmus M, Demirbilek S, et al. The use of magnesium to prevent laryngospasm after tonsillectomy and adenoidectomy: a preliminary study. Paediatr Anaesth. 2003;13(1):43-7. [PMID:12535038]
- ROSEN M. Atropine in the treatment of laryngeal spasm. Br J Anaesth. 1960;32:190-1. [PMID:14438892]
- HOLLIDAY MA, SEGAR WE. The maintenance need for water in parenteral fluid therapy. Pediatrics. 1957;19(5):823-32. [PMID:13431307]
- Bailey AG, McNaull PP, Jooste E, et al. Perioperative crystalloid and colloid fluid management in children: where are we and how did we get here? Anesth Analg. 2010;110(2):375-90. [PMID:19955503]
- Sümpelmann R, Becke K, Brenner S, et al. Perioperative intravenous fluid therapy in children: guidelines from the Association of the Scientific Medical Societies in Germany. Paediatr Anaesth. 2017;27(1):10-18. [PMID:27747968]
- Sümpelmann R, Mader T, Dennhardt N, et al. A novel isotonic balanced electrolyte solution with 1% glucose for intraoperative fluid therapy in neonates: results of a prospective multicentre observational postauthorisation safety study (PASS). Paediatr Anaesth. 2011;21(11):1114-8. [PMID:21564388]
- Lavoie J. Blood transfusion risks and alternative strategies in pediatric patients. Paediatr Anaesth. 2011;21(1):14-24. [PMID:21155923]
- Parker RI. Transfusion in critically ill children: indications, risks, and challenges. Crit Care Med. 2014;42(3):675-90. [PMID:24534955]
- Rouette J, Trottier H, Ducruet T, et al. Red blood cell transfusion threshold in postsurgical pediatric intensive care patients: a randomized clinical trial. Ann Surg. 2010;251(3):421-7. [PMID:20118780]
- Willems A, Harrington K, Lacroix J, et al. Comparison of two red-cell transfusion strategies after pediatric cardiac surgery: a subgroup analysis. Crit Care Med. 2010;38(2):649-56. [PMID:19789443]
- Cholette JM, Rubenstein JS, Alfieris GM, et al. Children with single-ventricle physiology do not benefit from higher hemoglobin levels post cavopulmonary connection: results of a prospective, randomized, controlled trial of a restrictive versus liberal red-cell transfusion strategy. Pediatr Crit Care Med. 2011;12(1):39-45. [PMID:20495502]
- American Society of Anesthesiologists. Statement on Practice Recommendations for Pediatric Anesthesia. asahq.org; accessed 2/21/17
- Coté CJ, Zaslavsky A, Downes JJ, et al. Postoperative apnea in former preterm infants after inguinal herniorrhaphy. A combined analysis. Anesthesiology. 1995;82(4):809-22. [PMID:7717551]
- Ozdemir T, Arıkan A. Postoperative apnea after inguinal hernia repair in formerly premature infants: impacts of gestational age, postconceptional age and comorbidities. Pediatr Surg Int. 2013;29(8):801-4. [PMID:23780479]
- Kelly CJ, Walker RW. Perioperative pulmonary aspiration is infrequent and low risk in pediatric anesthetic practice. Paediatr Anaesth. 2015;25(1):36-43. [PMID:25280003]
- Hampson-Evans D, Morgan P, Farrar M. Pediatric laryngospasm. Paediatr Anaesth. 2008;18(4):303-7. [PMID:18315635]
- Luce V, Harkouk H, Brasher C, et al. Supraglottic airway devices vs tracheal intubation in children: a quantitative meta-analysis of respiratory complications. Paediatr Anaesth. 2014;24(10):1088-98. [PMID:25074619]
- Salaün JP, Frykholm P, Poirel N, et al. Paediatric anaesthesia and the developing brain. Lancet Child Adolesc Health. 2026;10(10):765-776. [PMID:42537677]
- McCann ME, de Graaff JC, Dorris L, et al. Neurodevelopmental outcome at 5 years of age after general anaesthesia or awake-regional anaesthesia in infancy (GAS): an international, multicentre, randomised, controlled equivalence trial. Lancet. 2019;393(10172):664-677. [PMID:30782342]
- Sun LS, Li G, Miller TL, et al. Association Between a Single General Anesthesia Exposure Before Age 36 Months and Neurocognitive Outcomes in Later Childhood. JAMA. 2016;315(21):2312-20. [PMID:27272582]
- Warner DO, Zaccariello MJ, Katusic SK, et al. Neuropsychological and Behavioral Outcomes after Exposure of Young Children to Procedures Requiring General Anesthesia: The Mayo Anesthesia Safety in Kids (MASK) Study. Anesthesiology. 2018;129(1):89-105. [PMID:29672337]
- Reighard C, Junaid S, Jackson WM, et al. Anesthetic Exposure During Childhood and Neurodevelopmental Outcomes: A Systematic Review and Meta-analysis. JAMA Netw Open. 2022;5(6):e2217427. [PMID:35708687]
- Lo E, Kalish BT. Neurodevelopmental outcomes after neonatal surgery. Pediatr Surg Int. 2022;39(1):22. [PMID:36449183]
- Andropoulos DB, Greene MF. Anesthesia and Developing Brains - Implications of the FDA Warning. N Engl J Med. 2017;376(10):905-907. [PMID:28177852]
- Voelker R. Warnings for Anesthetic Drugs. JAMA. 2017;317(23):2363. [PMID:28632854]
- Agarwal R, Wang T, Diaz CD, et al. The Pediatrician's Role in the Evaluation and Preparation of Pediatric Patients Undergoing Anesthesia. Pediatrics. 2026;157(3). [PMID:41698393]
- Polaner DM, Taenzer AH, Walker BJ, et al. Pediatric Regional Anesthesia Network (PRAN): a multi-institutional study of the use and incidence of complications of pediatric regional anesthesia. Anesth Analg. 2012;115(6):1353-64. [PMID:22696610]
- Walker BJ, Long JB, De Oliveira GS, et al. Peripheral nerve catheters in children: an analysis of safety and practice patterns from the pediatric regional anesthesia network (PRAN). Br J Anaesth. 2015;115(3):457-62. [PMID:26205902]
- Ecoffey C, Lacroix F, Giaufré E, et al. Epidemiology and morbidity of regional anesthesia in children: a follow-up one-year prospective survey of the French-Language Society of Paediatric Anaesthesiologists (ADARPEF). Paediatr Anaesth. 2010;20(12):1061-9. [PMID:21199114]
- Salazar JH, Yang J, Shen L, et al. Pediatric malignant hyperthermia: risk factors, morbidity, and mortality identified from the Nationwide Inpatient Sample and Kids' Inpatient Database. Paediatr Anaesth. 2014. [PMID:24974921]
- Tiret L, Nivoche Y, Hatton F, et al. Complications related to anaesthesia in infants and children. A prospective survey of 40240 anaesthetics. Br J Anaesth. 1988;61(3):263-9. [PMID:3179147]
- Cohen MM, Cameron CB, Duncan PG. Pediatric anesthesia morbidity and mortality in the perioperative period. Anesth Analg. 1990;70(2):160-7. [PMID:2301747]
- Bhananker SM, Ramamoorthy C, Geiduschek JM, et al. Anesthesia-related cardiac arrest in children: update from the Pediatric Perioperative Cardiac Arrest Registry. Anesth Analg. 2007;105(2):344-50. [PMID:17646488]
- Posner KL, Geiduschek J, Haberkern CM, et al. Unexpected cardiac arrest among children during surgery, a North American registry to elucidate the incidence and causes of anesthesia related cardiac arrest. Qual Saf Health Care. 2002;11(3):252-7. [PMID:12486990]
- Kawashima Y, Seo N, Morita K, et al. Anesthesia-related mortality and morbidity in Japan (1999). J Anesth. 2002;16(4):319-31. [PMID:14517625]
- Flick RP, Gleich SJ, Herr MM, et al. The risk of malignant hyperthermia in children undergoing muscle biopsy for suspected neuromuscular disorder. Paediatr Anaesth. 2007;17(1):22-7. [PMID:17184427]
- Litman RS, Rosenberg H. Malignant hyperthermia: update on susceptibility testing. JAMA. 2005;293(23):2918-24. [PMID:15956637]
- https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=4df35098-8702-46be-ac67-30cfdf1aa570
- https://www.ncbi.nlm.nih.gov/books/NBK1146/
- Litman RS, Griggs SM, Dowling JJ, et al. Malignant Hyperthermia Susceptibility and Related Diseases. Anesthesiology. 2018;128(1):159-167. [PMID:28902673]
- American Society of Anesthesiologists Committee. Practice guidelines for preoperative fasting and the use of pharmacologic agents to reduce the risk of pulmonary aspiration: application to healthy patients undergoing elective procedures: an updated report by the American Society of Anesthesiologists Committee on Standards and Practice Parameters. Anesthesiology. 2011;114(3):495-511. [PMID:21307770]
- Bordet F, Allaouchiche B, Lansiaux S, et al. Risk factors for airway complications during general anaesthesia in paediatric patients. Paediatr Anaesth. 2002;12(9):762-9. [PMID:12519134]
- Brady M, Kinn S, Ness V, et al. Preoperative fasting for preventing perioperative complications in children. Cochrane Database Syst Rev. 2009. [PMID:19821343]
- Brambrink AM, Evers AS, Avidan MS, et al. Isoflurane-induced neuroapoptosis in the neonatal rhesus macaque brain. Anesthesiology. 2010;112(4):834-41. [PMID:20234312]
- Brunet-Wood K, Simons M, Evasiuk A, et al. Surgical fasting guidelines in children: Are we putting them into practice? J Pediatr Surg. 2016;51(8):1298-302. [PMID:27166876]
- Coté CJ, Wilson S, AMERICAN ACADEMY OF PEDIATRICS, et al. Guidelines for Monitoring and Management of Pediatric Patients Before, During, and After Sedation for Diagnostic and Therapeutic Procedures: Update 2016. Pediatrics. 2016;138(1). [PMID:27354454]
- Dabke T, Scott TE, Taylor B. Impact of preoperative fasting duration on perioperative complications in elective paediatric procedures: a systematic review and meta-analysis. Br J Anaesth. 2026;136(1):158-166. [PMID:41314944]
- Densmore JC, Peterson DB, Stahovic LL, et al. Initial surgical and pain management outcomes after Nuss procedure. J Pediatr Surg. 2010;45(9):1767-71. [PMID:20850618]
- Disma N, Frykholm P, Cook-Sather SD, et al. Pro-Con Debate: 1- vs 2-Hour Fast for Clear Liquids Before Anesthesia in Children. Anesth Analg. 2021;133(3):581-591. [PMID:34403386]
- Flick RP, Katusic SK, Colligan RC, et al. Cognitive and behavioral outcomes after early exposure to anesthesia and surgery. Pediatrics. 2011;128(5):e1053-61. [PMID:21969289]
- Gleich SJ, Flick R, Hu D, et al. Neurodevelopment of children exposed to anesthesia: design of the Mayo Anesthesia Safety in Kids (MASK) study. Contemp Clin Trials. 2015;41:45-54. [PMID:25555440]
- Green SM, Roback MG, Krauss B, et al. Predictors of airway and respiratory adverse events with ketamine sedation in the emergency department: an individual-patient data meta-analysis of 8,282 children. Ann Emerg Med. 2009;54(2):158-68.e1-4. [PMID:19201064]
- Grunwell JR, Travers C, McCracken CE, Scherrer PD, Stormorken AG, Chumpitazi CE, Roback MG, Stockwell JA, Kamat PP. Procedural Sedation Outside of the Operating Room Using Ketamine in 22,645 Children: A Report From the Pediatric Sedation Research Consortium. Pediatr Crit Care Med. 2016 Dec;17(12):1109-1116.
- Ikonomidou C, Bosch F, Miksa M, et al. Blockade of NMDA receptors and apoptotic neurodegeneration in the developing brain. Science. 1999;283(5398):70-4. [PMID:9872743]
- Jevtovic-Todorovic V, Absalom AR, Blomgren K, et al. Anaesthetic neurotoxicity and neuroplasticity: an expert group report and statement based on the BJA Salzburg Seminar. Br J Anaesth. 2013;111(2):143-51. [PMID:23722106]
- Jevtovic-Todorovic V, Hartman RE, Izumi Y, et al. Early exposure to common anesthetic agents causes widespread neurodegeneration in the developing rat brain and persistent learning deficits. J Neurosci. 2003;23(3):876-82. [PMID:12574416]
- Kamat PP, McCracken CE, Gillespie SE, et al. Pediatric critical care physician-administered procedural sedation using propofol: a report from the Pediatric Sedation Research Consortium Database. Pediatr Crit Care Med. 2015;16(1):11-20. [PMID:25340297]
- Lee BJ, August DA. COLDS: A heuristic preanesthetic risk score for children with upper respiratory tract infection. Paediatr Anaesth. 2014;24(3):349-50. [PMID:24372849]
- Llewellyn N, Moriarty A. The national pediatric epidural audit. Paediatr Anaesth. 2007;17(6):520-33. [PMID:17498013]
- Merchant R, Chartrand D, Dain S, et al. Guidelines to the Practice of Anesthesia - Revised Edition 2016. Can J Anaesth. 2016;63(1):86-112. [PMID:26576558]
- Rachel Homer J, Elwood T, Peterson D, et al. Risk factors for adverse events in children with colds emerging from anesthesia: a logistic regression. Paediatr Anaesth. 2007;17(2):154-61. [PMID:17238887]
- Schmitz A, Kellenberger CJ, Neuhaus D, et al. Fasting times and gastric contents volume in children undergoing deep propofol sedation--an assessment using magnetic resonance imaging. Paediatr Anaesth. 2011;21(6):685-90. [PMID:21414079]
- Slikker W, Zou X, Hotchkiss CE, et al. Ketamine-induced neuronal cell death in the perinatal rhesus monkey. Toxicol Sci. 2007;98(1):145-58. [PMID:17426105]
- Smith I, Kranke P, Murat I, et al. Perioperative fasting in adults and children: guidelines from the European Society of Anaesthesiology. Eur J Anaesthesiol. 2011;28(8):556-69. [PMID:21712716]
- Splinter WM, Stewart JA, Muir JG. Large volumes of apple juice preoperatively do not affect gastric pH and volume in children. Can J Anaesth. 1990;37(1):36-9. [PMID:2403851]
- St Peter SD, Weesner KA, Weissend EE, et al. Epidural vs patient-controlled analgesia for postoperative pain after pectus excavatum repair: a prospective, randomized trial. J Pediatr Surg. 2012;47(1):148-53. [PMID:22244408]
- Waldman RA, Willis S. A simplified approach to ultrasound guided ilioinguinal nerve block. Phys Med Rehabil Res. 2016;1.
- Waldman RA, Willis S. A simplified approach to ultrasound guided ilioinguinal nerve block. Phys Med Rehabil Res. 2016;1.
- Weber T, Mätzl J, Rokitansky A, et al. Superior postoperative pain relief with thoracic epidural analgesia versus intravenous patient-controlled analgesia after minimally invasive pectus excavatum repair. J Thorac Cardiovasc Surg. 2007;134(4):865-70. [PMID:17903498]
- Wilder RT, Flick RP, Sprung J, et al. Early exposure to anesthesia and learning disabilities in a population-based birth cohort. Anesthesiology. 2009;110(4):796-804. [PMID:19293700]
- Zadrazil M, Feigl G, Opfermann P, et al. Ultrasound-Guided Dorsal Penile Nerve Block in Children: An Anatomical-Based Observational Study of a New Anesthesia Technique. Children (Basel). 2023;11(1). [PMID:38255363]
- Zhang H, Du L, Du Z, et al. Association between childhood exposure to single general anesthesia and neurodevelopment: a systematic review and meta-analysis of cohort study. J Anesth. 2015;29(5):749-57. [PMID:26002228]